

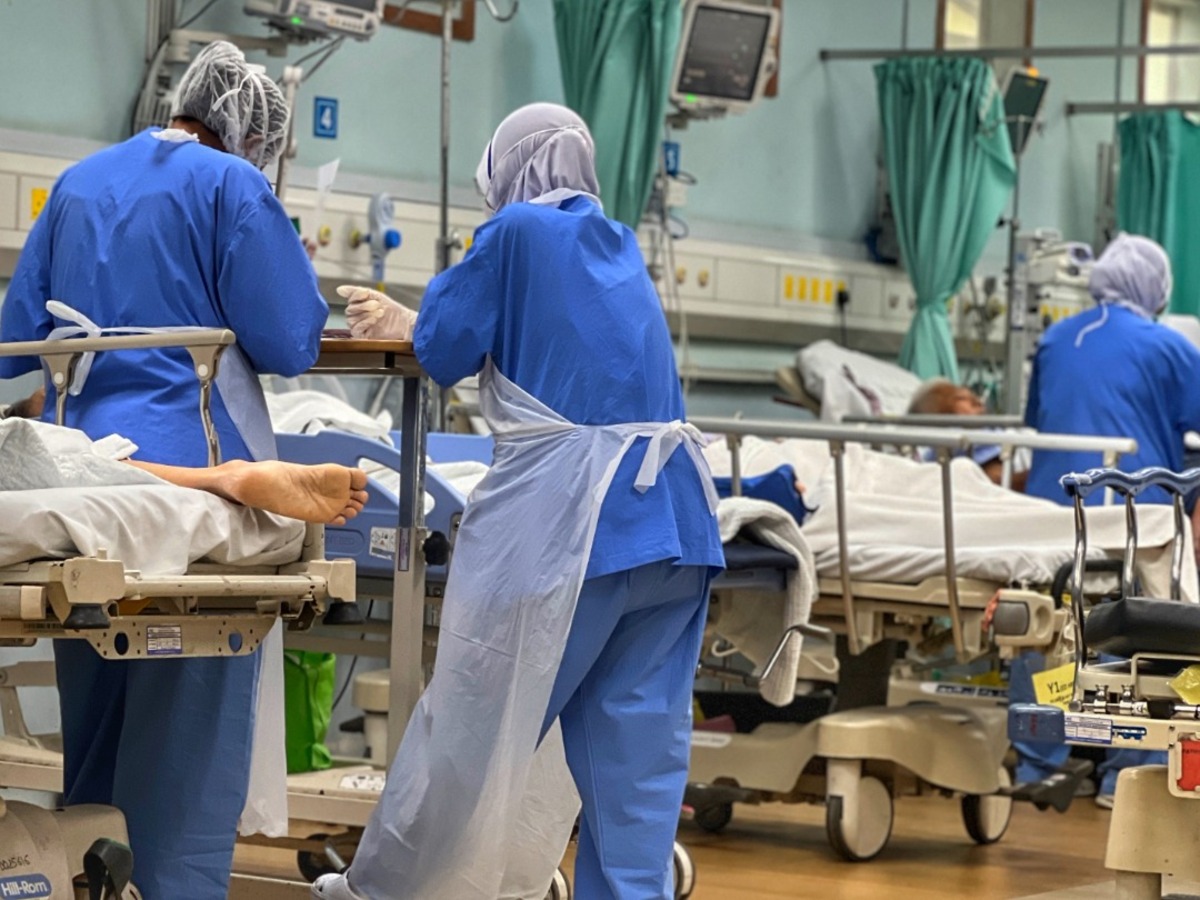
Years ago, when I was working as an ICU nurse, I cared for a paediatric patient who remained critically ill for an extended period. During that time, my own life changed in ways that made me understand the family’s situation more deeply. I came to know the patient’s routines and the family’s cycle of fear and hope.
When the patient eventually died, I knew what I had to do. I remained calm, supported the family and completed my responsibilities. But I was grieving too. I stepped into the treatment room, cried privately, wiped my tears and returned to the family.
My grief was not the same as the family’s, and I would never compare the two. They had lost someone they loved. Mine was the grief of a nurse who had cared for the same patient over time and witnessed repeated struggles for survival.
This emotional response is known as professional grief. It may appear as sadness, helplessness, guilt or emotional exhaustion. Yet it often remains unspoken because nurses are expected to stay composed and continue working.
At the time, I did what many nurses do, I pulled myself together and finished the shift. A patient’s death does not pause the work around us. A nurse may support the family, prepare the patient’s body and then immediately care for another critically ill person. There may be no time to acknowledge the loss, and repeated experiences of this kind can accumulate quietly.
Today, a nurse may turn to Threads, TikTok, or Instagram after a difficult shift. That is not necessarily wrong. Social media can offer connection, allow nurses to name their feelings and remind them that they are not alone.
The boundary is confidentiality. Emotions may be shared, but identifiable details about a patient, family, hospital or clinical event must remain private. Share the feeling, not the patient’s story.
There is no single correct place for grief. A nurse may talk to a trusted colleague, seek confidential counselling, write privately, pray, rest or share a general reflection online. What matters is having a safe way to acknowledge the loss without harming the patient’s privacy or carrying the grief alone.
Nurses should also recognise when grief is no longer easing. Persistent sleep problems, intrusive memories, overwhelming guilt, emotional numbness or difficulty functioning at work may signal a need for professional support. Asking for help is not an admission of incompetence. It helps protect personal wellbeing and the ability to provide safe care.
Nurses should not be expected to manage this alone. Their colleagues, managers and hospitals also have a role. After a difficult death, support could begin with a private check-in, a brief and blame-free debriefing, access to trained peer supporters and a confidential referral pathway. It must also be accessible to nurses working nights and rotating shifts.
Colleagues do not need perfect words, they can simply ask, “Do you need a moment?” That small question recognises the nurse as a person, not only as a professional expected to keep functioning.
The public should understand this too. Nurses do not become emotionally detached simply because death is part of their work. Their grief does not compete with the family’s loss, but it still deserves recognition.
The monitor may go silent, but the memory does not. It can follow a nurse to the next bedside, the next shift and, sometimes, years into the future. Grief cannot simply be hidden until it disappears.
We teach ICU nurses how to respond when life is ending. We must also support them in living with what remains. When the monitor goes silent, the nurse continues, and no nurse should carry that silence alone.
Identifying details have been omitted to protect the confidentiality of the patient and family. The author is a lecturer at the Faculty of Nursing, Universiti Malaya.
- This is the personal opinion of the writer or publication and does not necessarily represent the views of CodeBlue.

